






One scheduling gap can [cancel a case]
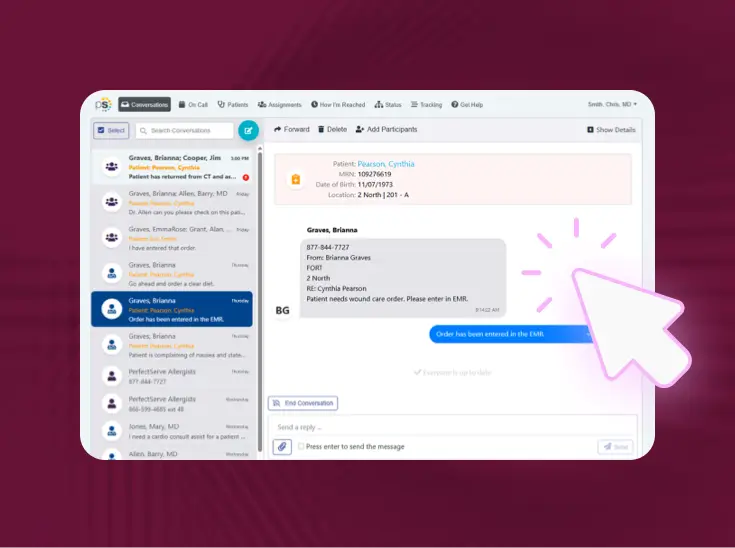
Block schedules are often built manually, separate from your ASC's live schedule. When cases, rooms, or staffing change, those updates don't automatically sync, making coverage gaps easy to miss until the day of surgery.
What changes when scheduling stops being manual


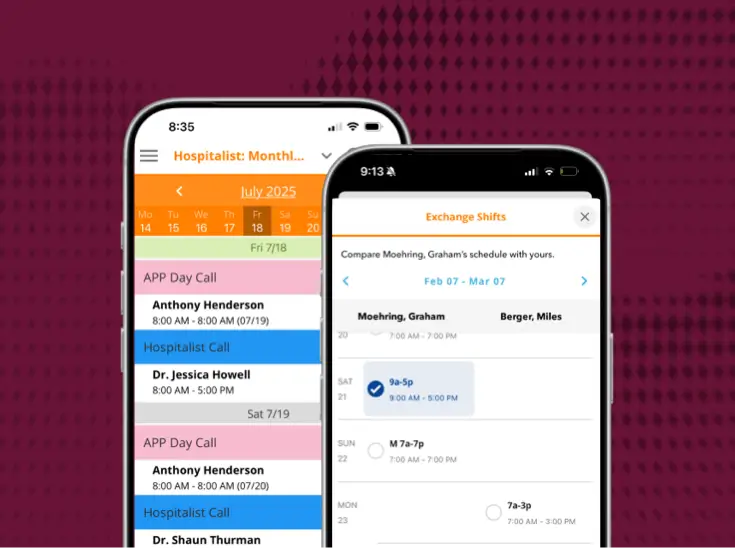
Block time, call rotation, and anesthesia coverage in one system.
OR and block scheduling
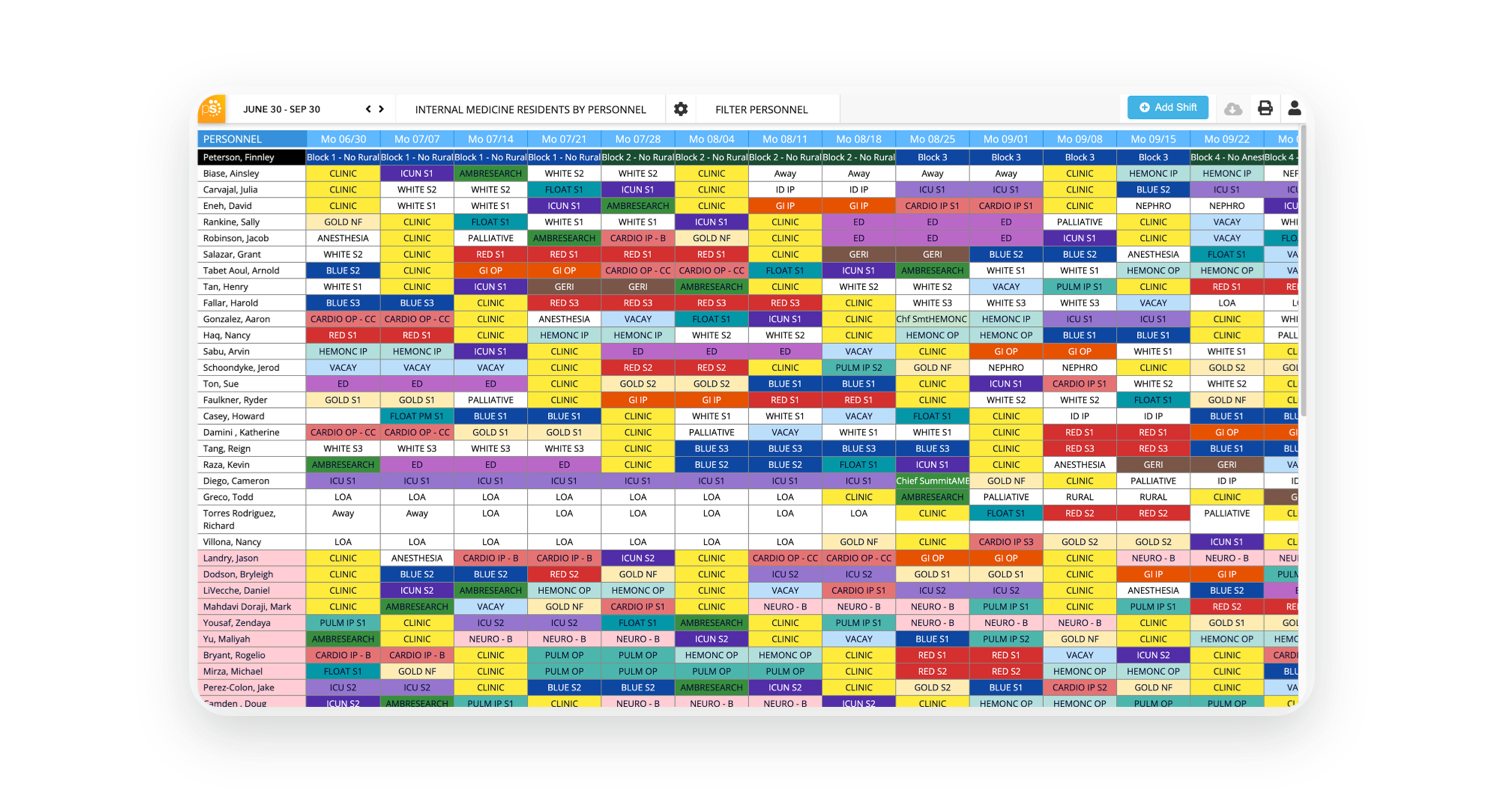
Call rotation and anesthesia coverage
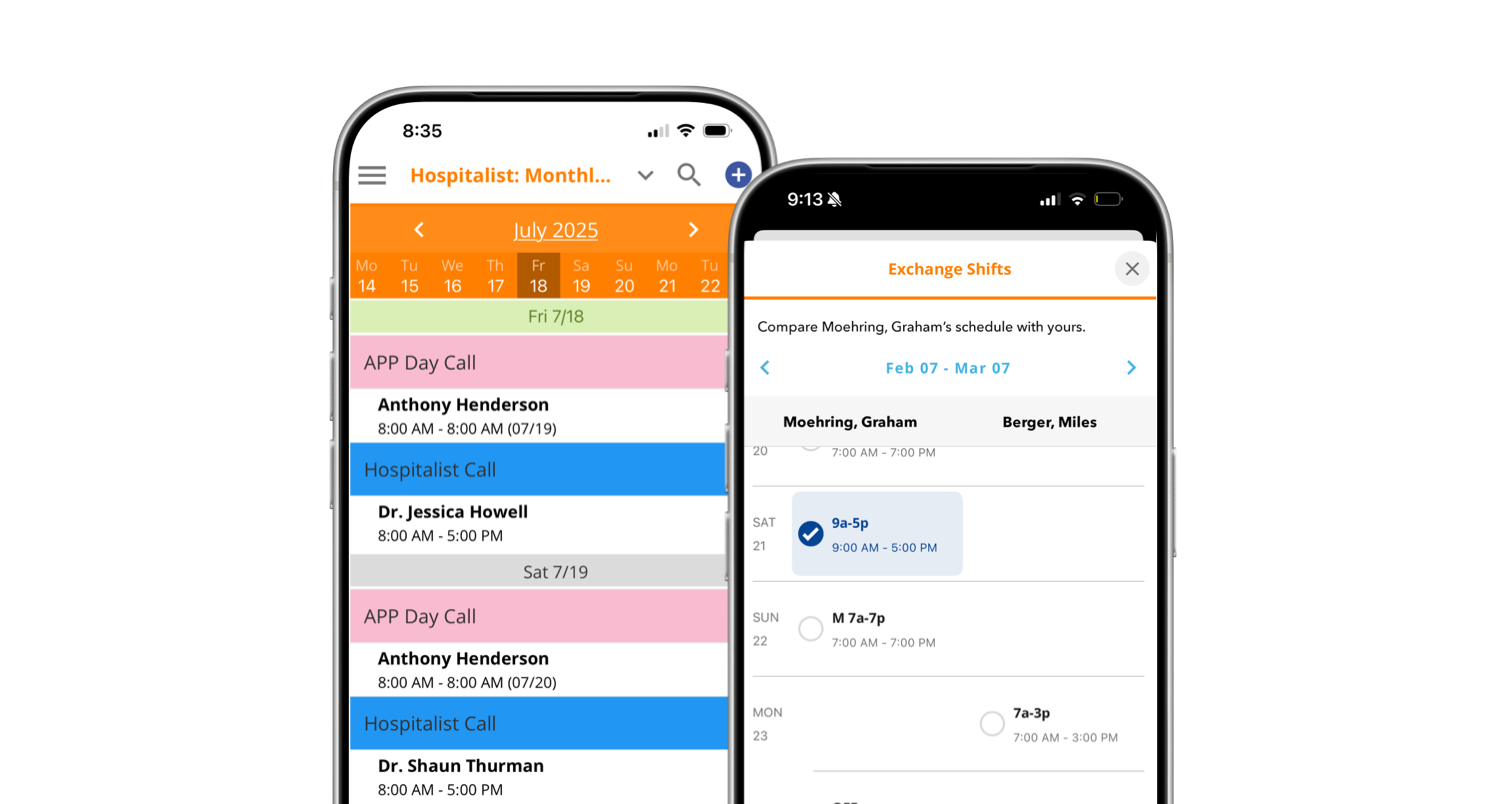

What happens when a CRNA needs coverage next day
Initiate time-off request
Request received
Switch is auto-approved
The case stays on track
Built for how surgical groups scale



Your rules stay intact as the group grows

No key-person dependency

Support that builds it with you

Standardization without a takeover
What surgical groups and ASC leaders ask first
What separates PerfectServe from every other platform on this list?
The clearest differentiator is that PerfectServe’s scheduling and communication systems share the same underlying data. When a schedule changes, routing updates automatically. That means no manual intervention, no lag, no staff member chasing down who’s actually on call. Most platforms on this list handle either scheduling or communication well. PerfectServe is built so the two functions inform each other in real time.
What results have PerfectServe customers seen?
Advocate Good Samaritan Hospital reported a 99% decrease in overhead physician pages, Hospital for Special Surgery cut rapid response times 73% (2:30 → 40 sec), and Munson Healthcare’s 7-hospital system retired 600 pagers (~$120K/yr saved) and cut 56,000 calls over 13 months.
How much does PerfectServe cost?
PerfectServe uses custom pricing based on organization size and the solutions you need, such as clinical communication, scheduling, operator console, or medical answering service. Request a demo for a quote tailored to your environment.
Can PerfectServe replace our pagers?
Yes. PerfectServe runs on the devices teams already use (smartphones, desktops, and VoIP phones) and can work alongside legacy pagers during a transition rather than forcing an overnight switch. Organizations commonly use it to retire pager fleets while keeping critical alerts reliable.
Does PerfectServe integrate with our EHR and existing systems?
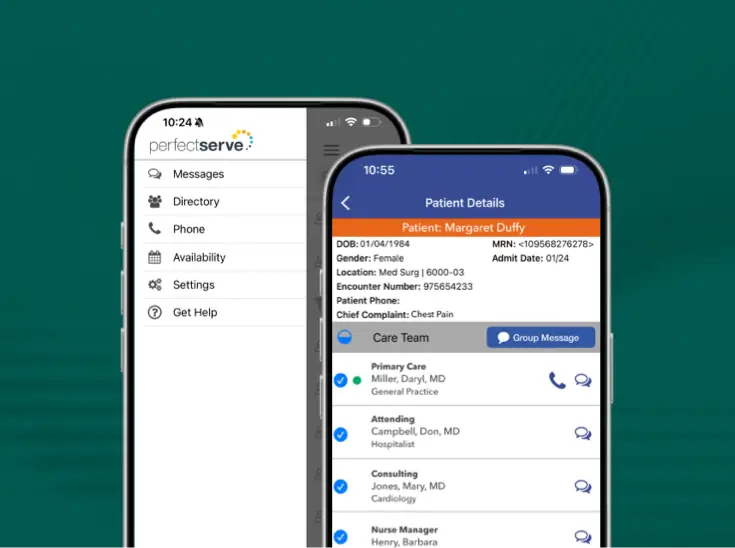
Yes. PerfectServe integrates with Epic, Oracle Health (Cerner), and 270+ clinical systems, including nurse call and alerting platforms, lab and radiology systems, telephony providers, and pager networks. Messaging can be embedded directly in the EHR, so patient context travels with every on-call message and clinicians don’t switch between applications.
Is clinical communication software only for large hospitals?
No. The best platforms can scale from single-specialty clinics to large health systems. PerfectServe serves both 500+ hospitals and 30,000+ medical practices, using the same routing engine for acute and post-acute care settings.
Is PerfectServe HIPAA-compliant and secure?
Yes. PerfectServe is HIPAA compliant and SOC 2 compliant. Messages are encrypted at rest and in flight, every action is captured in a complete audit trail, and every covered entity receives a signed Business Associate Addendum before going live. See how we make trust and security a priority.
How long does a demo take?
A demo with PerfectServe typically lasts about 20-30 minutes. Schedule one now to see how our solutions can benefit your organization.
Don’t have time? Take a product tour of our solutions.
Do I need a special device to use PerfectServe?
No. PerfectServe works on your legacy devices, smartphones (including both BYOD and shared device models), VoIP and landline phones, desktops, and even pagers. No proprietary devices are required.
What is PerfectServe?
PerfectServe is a leading provider of technology that helps healthcare organizations communicate, coordinate real-time care delivery, and schedule their most valuable assets, including people, rooms, and even equipment. With our clinical communication, physician scheduling, operator console, and medical answering service solutions, we help our customers accelerate speed to care by ensuring the right people are in place at the right time to take action on important information related to patient care.
How is this different from a spreadsheet or another scheduling tool?
Lightning Bolt is built specifically for physician and staff scheduling. It applies your group's own rules for call rotation, and anesthesia coverage automatically, instead of you rebuilding those rules by hand every scheduling cycle.
If a management company standardizes scheduling across our centers, do surgeons lose control of their own schedules?
No. Surgeon and department-level rules stay local. Operations gets one view across every center while each surgical group's schedule continues to follow their own rules and preferences.
Is every schedule change documented on one record?
Yes. Every schedule change is captured with time stamps: what changed, who covers now, and when the change was made. Some schedule changes can be automated, while other changes can be flagged for approval before they're made.
Does your solution know which locations my providers are credentialed for?
Yes, Lightning Bolt allows you to select which assignments (locations) each individual is able to be scheduled for. This applies to automated scheduling as well as manual changes.
Can the system schedule nurses, technicians, or physician assistants (PAs)?
Yes, our system is flexible enough to schedule any staff.
